Medical note: This article is for educational purposes only and should not replace care from a neurologist, geneticist, metabolic specialist, or other qualified clinician.
What Is Leukodystrophy?
Leukodystrophy is not one disease. It is a family reunion of rare neurological disorders, and unfortunately, nobody brought the fun snacks. These conditions mainly affect the brain’s white matter, the part of the nervous system packed with nerve fibers that help different brain regions communicate. Many leukodystrophies damage or disrupt myelin, the protective coating around nerves that works a bit like insulation around an electrical wire.
When myelin is missing, poorly formed, or gradually destroyed, nerve signals can slow down, misfire, or stop traveling efficiently. That is why leukodystrophy symptoms often involve movement, balance, speech, vision, hearing, learning, behavior, seizures, or developmental regression. In children, families may notice that a child stops reaching milestones or loses skills they previously had. In adults, symptoms can be sneakier and may look like multiple sclerosis, psychiatric illness, unexplained walking problems, or progressive stiffness.
The word itself sounds like it escaped from a medical spelling bee: leuko means white, and dystrophy means abnormal growth or degeneration. Put together, leukodystrophy means a disorder of white matter development or maintenance.
Why White Matter Matters
White matter is the brain’s communication highway. Gray matter does much of the thinking, processing, and decision-making, while white matter helps send messages from one region to another. If gray matter is the office, white matter is the Wi-Fi, power cable, and hallway system all at once. When that network breaks down, the effects can show up throughout the body.
Because leukodystrophies affect the nervous system, symptoms can be widespread. A single genetic change may influence muscle tone, swallowing, learning, vision, adrenal function, and coordination. That is one reason diagnosis can be complicated. Doctors are not just looking for one symptom; they are trying to understand a pattern.
Common Types of Leukodystrophy
There are many forms of leukodystrophy, and new genetic causes continue to be identified. Some of the better-known types include:
Metachromatic Leukodystrophy
Metachromatic leukodystrophy, often shortened to MLD, is caused by problems with the body’s ability to break down certain fatty substances called sulfatides. These substances build up and damage myelin-producing cells. MLD may appear in infancy, childhood, adolescence, or adulthood. Earlier-onset forms are usually more severe.
X-Linked Adrenoleukodystrophy
X-linked adrenoleukodystrophy, or X-ALD, is caused by changes in the ABCD1 gene. It leads to the buildup of very long-chain fatty acids, especially affecting the brain, spinal cord, adrenal glands, and sometimes the testes. Boys may develop a rapidly progressive cerebral form, while some adults develop spinal cord symptoms. Females who carry an ABCD1 variant may also develop symptoms later in life, often involving stiffness, walking difficulty, or bladder problems.
Krabbe Disease
Krabbe disease, also called globoid cell leukodystrophy, is linked to low activity of the GALC enzyme. It causes toxic substances to accumulate and damage myelin. Infantile Krabbe disease can progress quickly, while later-onset forms may progress more slowly.
Canavan Disease
Canavan disease is caused by variants in the ASPA gene and is associated with problems breaking down N-acetylaspartic acid. Babies may develop poor head control, low muscle tone, developmental delay, seizures, feeding problems, and an enlarged head.
Alexander Disease
Alexander disease usually involves changes in the GFAP gene. It can affect infants, children, or adults. Symptoms may include developmental delay, seizures, swallowing problems, stiffness, speech changes, and abnormal brain MRI findings.
What Causes Leukodystrophy?
The main cause of leukodystrophy is genetic change. In most cases, a mutation affects a protein, enzyme, transporter, or structural component needed to build or maintain healthy white matter. The result may be poor myelin formation, myelin breakdown, toxic buildup, inflammation, or failure of cells to perform their usual maintenance work.
Leukodystrophies can be inherited in different ways. Some are autosomal recessive, meaning a child usually needs to inherit one changed gene from each parent. Others are X-linked, meaning the gene is on the X chromosome. Some are autosomal dominant, where one changed copy of a gene can cause disease. Occasionally, a genetic change happens for the first time in the affected person, with no known family history.
This is important: a lack of family history does not rule out leukodystrophy. Rare genetic conditions can appear unexpectedly, especially when both parents silently carry a recessive variant or when a new mutation occurs.
Symptoms of Leukodystrophy
Symptoms vary widely depending on the specific type, age of onset, and speed of progression. Some babies show signs early. Some children appear healthy for years before symptoms emerge. Some adults may spend a long time with vague neurological problems before anyone connects the dots.
Symptoms in Babies and Children
In infants and children, possible symptoms include delayed milestones, loss of previously learned skills, poor feeding, vomiting, irritability, abnormal muscle tone, trouble sitting or walking, seizures, vision problems, hearing loss, swallowing difficulty, abnormal eye movements, learning difficulties, and changes in behavior.
Parents may describe a child who was developing normally and then began to plateau or regress. That regression is often one of the biggest warning signs. When a child loses speech, motor ability, or social engagement, clinicians usually investigate carefully for neurological, metabolic, genetic, and developmental causes.
Symptoms in Adults
Adult-onset leukodystrophy can be especially tricky. Symptoms may include progressive walking difficulty, stiffness in the legs, poor balance, bladder urgency, tremor, cognitive decline, psychiatric symptoms, personality changes, neuropathy, vision issues, or speech problems.
Because adult symptoms may overlap with multiple sclerosis, hereditary spastic paraplegia, dementia, psychiatric illness, or vitamin deficiencies, diagnosis can take time. When symptoms progress steadily and MRI shows unusual white matter changes, doctors may consider genetic leukodystrophy as part of the differential diagnosis.
How Leukodystrophy Is Diagnosed
Diagnosing leukodystrophy is a detective story, except the detective wears a white coat and orders tests instead of dramatically removing sunglasses. The goal is to identify the exact type, because treatment options, prognosis, family counseling, and clinical trial eligibility may depend on the specific diagnosis.
Medical History and Neurological Exam
The first step is usually a detailed history. Doctors ask about development, school performance, movement, seizures, feeding, behavior, family history, ethnic background, pregnancy and birth history, and whether symptoms are stable or worsening. A neurological exam checks reflexes, strength, tone, coordination, walking, eye movements, sensation, and cognition.
MRI of the Brain and Spine
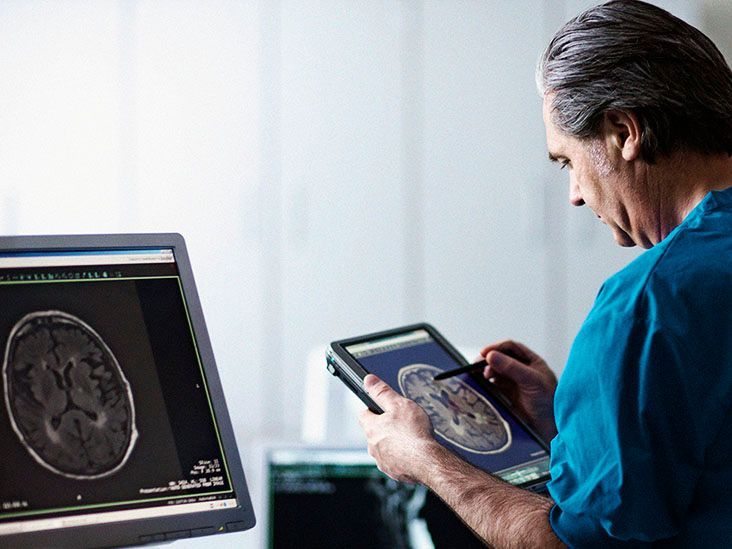
Magnetic resonance imaging, or MRI, is one of the most important tools. Leukodystrophies often create recognizable white matter patterns. Radiologists and neurologists look at which regions are affected, whether the pattern is symmetrical, whether contrast enhancement is present, and whether the cerebellum, brainstem, spinal cord, or peripheral nerves may be involved.
MRI does not always give the final answer, but it can point the medical team toward the right category of disease. In some leukodystrophies, MRI changes may appear before major symptoms, which is why screening and early monitoring can matter so much.
Genetic Testing
Genetic testing has changed the leukodystrophy landscape. Doctors may order a single-gene test, a leukodystrophy gene panel, whole-exome sequencing, or whole-genome sequencing. A confirmed genetic diagnosis can end years of uncertainty, guide treatment decisions, identify relatives who may be at risk, and help families understand recurrence risk in future pregnancies.
Blood, Urine, and Enzyme Tests
Depending on the suspected type, clinicians may order metabolic testing. Blood tests may measure very long-chain fatty acids for X-ALD, enzyme activity for MLD or Krabbe disease, adrenal function, inflammatory markers, vitamin levels, or other biochemical clues. Urine tests may help detect abnormal metabolites.
Newborn Screening
Newborn screening for leukodystrophy varies by state and condition. X-linked adrenoleukodystrophy is included in many U.S. newborn screening programs. Krabbe disease screening is available in some states. Screening for metachromatic leukodystrophy has also gained attention because early treatment may work best before severe symptoms appear. The key point is simple: when a treatable leukodystrophy is found early, the medical clock starts in a much better place.
Treatment for Leukodystrophy
There is no universal cure for all leukodystrophies. Treatment depends on the exact diagnosis, stage of disease, symptoms, age, MRI findings, and overall health. Some therapies aim to slow disease progression. Others focus on comfort, function, nutrition, mobility, communication, and quality of life.
Supportive and Symptom-Based Care
Supportive care is not “doing nothing.” It is often the difference between chaos and a coordinated life. A care plan may include anti-seizure medication, treatment for spasticity, physical therapy, occupational therapy, speech therapy, feeding support, respiratory care, pain management, sleep support, orthopedic care, educational services, and assistive technology.
For swallowing problems, a feeding evaluation can reduce the risk of choking or aspiration. For mobility issues, braces, walkers, wheelchairs, and adaptive seating may preserve independence and safety. For communication challenges, speech-language therapy and communication devices can help children and adults express needs, preferences, and personality.
Hematopoietic Stem Cell Transplant
Hematopoietic stem cell transplant, sometimes called HSCT, may help selected patients with certain leukodystrophies, especially when performed very early. It has been used in conditions such as cerebral X-ALD, Krabbe disease, and some cases of MLD. The idea is that donor-derived cells may provide enzyme or immune-system support that slows damage in the nervous system.
HSCT is not simple. It can involve chemotherapy, infection risk, graft-versus-host disease, hospital stays, and serious complications. Timing is crucial. In many leukodystrophies, transplant is most useful before advanced neurological decline has occurred. That is why specialist evaluation is essential.
Gene Therapy
Gene therapy has turned some leukodystrophy conversations from “nothing can be done” to “what stage are we in, and is this patient eligible?” That is a major shift. For selected children with metachromatic leukodystrophy, an FDA-approved gene therapy called atidarsagene autotemcel, sold as Lenmeldy, is available for specific early disease stages. For selected boys with early, active cerebral adrenoleukodystrophy who do not have a matched donor for allogeneic transplant, Skysona is an FDA-approved gene therapy designed to slow neurological progression.
These treatments are highly specialized and are not appropriate for every patient. They also carry serious risks and require expert evaluation, long-term monitoring, and careful discussion of benefits and uncertainties. Gene therapy is exciting, but it is not a magic wand. It is more like a very advanced aircraft: powerful, complex, expensive, and absolutely not something you fly without a trained crew.
Adrenal Treatment in X-ALD
In X-linked adrenoleukodystrophy, adrenal insufficiency is common, especially in males. This can be life-threatening if missed. Endocrinology care may include regular adrenal testing and hormone replacement when needed. Treating adrenal insufficiency does not cure the brain or spinal cord disease, but it can prevent adrenal crisis and improve safety.
Rehabilitation and Daily Function
Rehabilitation is central to leukodystrophy care. Physical therapy may focus on stretching, posture, balance, transfers, and mobility. Occupational therapy helps with daily activities such as dressing, bathing, writing, feeding, and adaptive equipment. Speech therapy may address speech, swallowing, cognition, and communication tools.
Good rehabilitation is practical. It asks: How can this person move safely? How can they eat comfortably? How can they communicate? How can school or work adapt? How can caregivers avoid injury? These questions may not sound as dramatic as gene therapy, but they shape everyday life.
Living With Leukodystrophy
A leukodystrophy diagnosis affects the whole family. The patient may need medical specialists, therapy appointments, school support, insurance navigation, genetic counseling, and emotional care. Parents may become part-time nurses, researchers, appointment coordinators, insurance negotiators, and professional bag-packers. If there were an Olympic event for organizing medical binders, many leukodystrophy families would medal.
Care teams often include neurologists, geneticists, metabolic specialists, rehabilitation doctors, physical therapists, occupational therapists, speech-language pathologists, dietitians, pulmonologists, endocrinologists, ophthalmologists, social workers, psychologists, palliative care specialists, and primary care clinicians. The best care is coordinated, not scattered.
Prognosis: What Families Want to Know
Prognosis depends heavily on the type of leukodystrophy and when symptoms begin. Some infantile forms progress rapidly. Some juvenile forms progress over years. Some adult-onset leukodystrophies move slowly but still cause meaningful disability. Early diagnosis may improve options, especially when a disease-specific therapy exists.
Families often ask, “How fast will this progress?” Sometimes doctors can answer with reasonable confidence based on the exact diagnosis. Other times, the answer is less certain. That uncertainty can be emotionally exhausting. It is one reason connecting with leukodystrophy specialty centers and patient organizations can be so valuable.
When to Seek Medical Evaluation
Medical evaluation is important when a child loses developmental skills, develops unexplained seizures, has progressive walking difficulty, shows new swallowing problems, develops abnormal muscle stiffness, or has unusual MRI findings. Adults should also seek evaluation for progressive neurological symptoms, especially if MRI shows white matter changes that do not fit a typical pattern.
Because some leukodystrophies have time-sensitive treatments, unexplained regression or progressive white matter disease deserves prompt attention. Waiting for symptoms to “sort themselves out” is not a great strategy when the brain is sending warning flares.
Research and the Future of Treatment
Leukodystrophy research is moving quickly. Scientists are studying gene therapy, enzyme replacement, substrate reduction, stem cell approaches, newborn screening, biomarkers, better MRI scoring, and natural history data. Natural history studies are especially important because rare diseases need careful tracking to understand what changes are caused by treatment and what changes would have happened anyway.
Families may ask about clinical trials. Eligibility depends on diagnosis, age, symptoms, MRI findings, previous treatments, and location. A leukodystrophy specialist can help determine whether a trial is realistic or appropriate.
Experience Section: What the Leukodystrophy Journey Often Feels Like
The experience of leukodystrophy rarely begins with a neat diagnosis. More often, it begins with a small concern that refuses to stay small. A toddler stops using words they once knew. A child who used to run begins tripping. A teenager develops unexplained stiffness. An adult notices that walking across a parking lot now requires the concentration of a chess tournament. At first, everyone hopes it is temporary. Maybe it is fatigue. Maybe it is growth. Maybe it is stress. Then the pattern continues.
For many families, the diagnostic journey is one of the hardest parts. Appointments pile up. One specialist says “developmental delay.” Another suggests therapy. Someone orders an MRI, and suddenly the conversation changes. White matter abnormalities appear on the scan, and the family enters a new vocabulary: myelin, leukodystrophy, genetic panel, enzyme assay, variant of uncertain significance. It can feel like being dropped into a foreign country where everyone speaks fluent medical Latin.
One common experience is the strange mix of relief and fear that comes with a diagnosis. Relief, because the mystery finally has a name. Fear, because the name is rare, serious, and often difficult to treat. Families may spend nights reading medical papers, patient stories, and treatment options. Some information is helpful. Some is outdated. Some is terrifying. A good care team helps turn that information storm into a plan.
Daily life may change in practical ways. A family might rearrange the house to reduce falls, learn how to stretch tight muscles, modify meals for safer swallowing, or coordinate school accommodations. A wheelchair or feeding tube can feel emotionally heavy at first, but many families later see these tools differently: not as symbols of defeat, but as equipment that protects comfort, safety, and participation.
Patients and caregivers also learn the importance of small wins. A calmer night of sleep matters. A successful therapy session matters. A communication device that lets a child choose a song matters. An adult with leukodystrophy who can keep working with accommodations may gain not only income, but dignity and routine. In rare disease care, progress is not always dramatic. Sometimes progress is a better chair, fewer choking episodes, a medication adjustment, or a school team that finally understands the plan.
Emotionally, leukodystrophy asks families to live in two timelines. One timeline is medical: test results, scans, treatment windows, appointments, and long-term planning. The other timeline is ordinary life: birthdays, movies, pets, homework, jokes, messy kitchens, and the ongoing human need to enjoy today. Families often become experts at holding both. They fight for treatment while still trying to make dinner. They discuss genetics and then argue about where the missing sock went. The disease is serious, but life does not become only disease.
Support matters. Leukodystrophy specialty centers, genetic counselors, therapists, social workers, patient advocacy groups, and other families can make the path less lonely. No article can make leukodystrophy easy. But accurate information, early diagnosis, coordinated care, and compassionate support can make the path clearer.
Conclusion
Leukodystrophy is a group of rare genetic disorders that affect the brain’s white matter and often disrupt myelin, the protective system that helps nerves communicate. The causes are usually inherited or new genetic changes, but the symptoms, age of onset, and progression can vary dramatically. Diagnosis often requires MRI, genetic testing, metabolic studies, neurological evaluation, and sometimes newborn screening results.
Treatment is changing. Supportive care remains essential for comfort, function, nutrition, communication, and quality of life. For selected leukodystrophies, therapies such as hematopoietic stem cell transplant, adrenal hormone replacement, and gene therapy may slow progression or improve outcomes when used at the right stage. The most important message is not to wait in confusion. When leukodystrophy is suspected, early referral to specialists can help families understand the diagnosis, evaluate treatment options, and build a care plan that respects both medical reality and everyday life.